
【探泌】前列腺应用解剖精粹(三)
编者按
在过去的几十年中,随着对前列腺解剖认识的不断加深以及手术技术的飞速发展,前列腺癌手术治疗的肿瘤控制和功能结果得到了显著改善。为帮助泌尿科医生了解根治性前列腺切除术涉及的解剖结构,并正确应用其中的命名术语,European Urology杂志发文(PMID:19931974)对前列腺及其周围结构作了详细描述。
本专栏对原文作了编译,并对原文图片作了高清化和中文标注。全部内容分为3期,本文为第三期,介绍不同筋膜层面分离技术(筋膜内分离、筋膜间分离及筋膜外分离)、膀胱前列腺肌(VPM)、盆底肌肉系统、尿道外括约肌、前列腺尖部形状。因译者水平有限,译文难免存在不准确的地方,欢迎各位同道指正。
01 不同筋膜层面分离技术
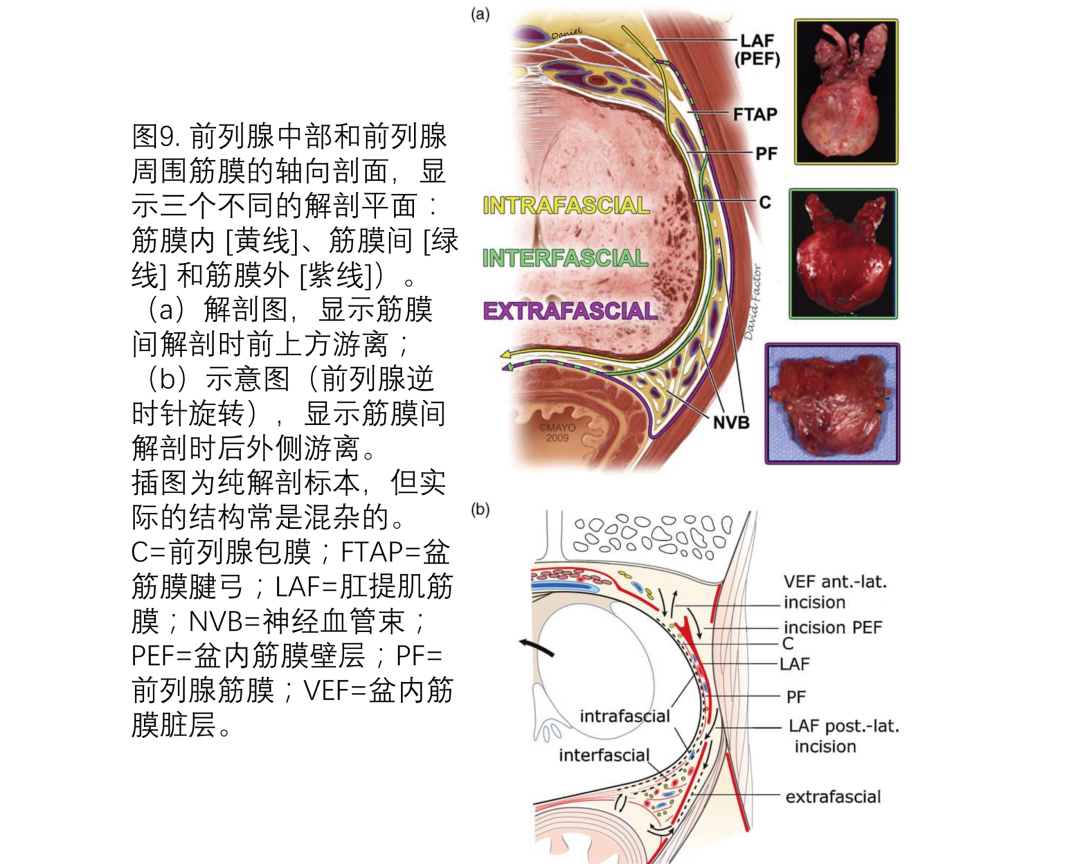
前列腺的筋膜和神经解剖对根治性前列腺切除术具有重要意义,尤其是筋膜代表了重要的手术分离层面。根据术中选择的分离层面,会有几种技术上的变化(图9)。以下描述了不同手术分离层面的解剖学含义。
1.Intrafascial dissection(筋膜内分离)
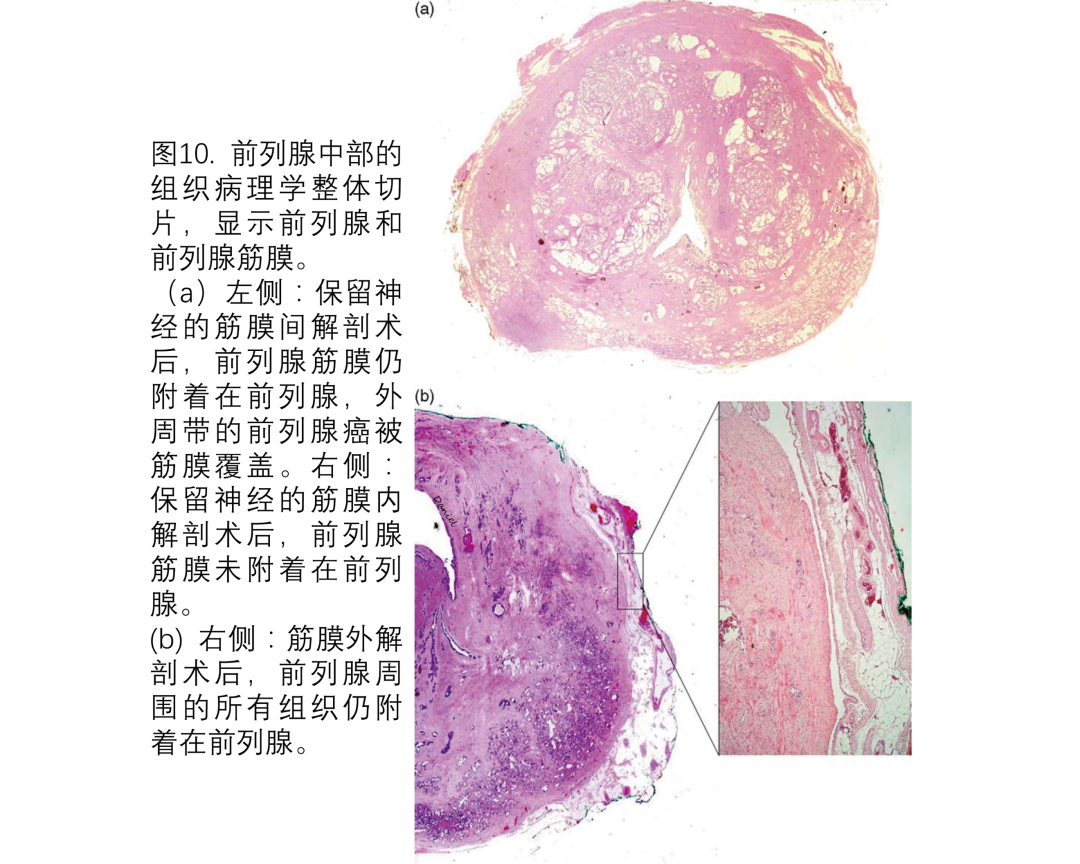
NVB的筋膜内分离是沿着前列腺包膜层面分离,分离层面在前列腺前外侧和后外侧时位于PF内侧或内部,以及pPF/SVF前方(图9和10)。尽管如此,部分pPF/SVF通常仍保留在前列腺标本的后表面,与中线的包膜融合。从6点钟位置开始顺行分离时,可能会发现一个更容易分离的层面,因为在这个水平上,pPF/SVF较厚并且可以更容易地识别为单层结构。从侧方高位进入时,由于筋膜呈多层分布,尤其是在前列腺后外侧边界处,该层面可能更难识别。筋膜内入路可对外侧PF进行全层保留,NVB位于PF外侧且被PF覆盖,因此能够完全保留NVB。在手术结束时,NVB所在的前列腺包膜后外侧和外侧表面将没有PF及部分pPF/SVF(图10)。筋膜内分离时不慎突破包膜的风险是最大的。
2.Interfascial dissection(筋膜间分离)
NVB的筋膜间分离是在PF外部或外侧分离前列腺前外侧和后外侧,同时在前列腺轴面5、7点钟位置或2、10点钟位置NVB的内侧分离。通过将完整的NVB移出前列腺,从而使前列腺后外侧仍被筋膜覆盖(图9和10)。根据解剖学差异,该技术可能更倾向于切除部分NVB,因为这种分离方法不一定能保留分散在前列腺前外侧表面的所有神经纤维。外侧PF保留在前列腺而不是附着在NVB,pPF/SVF保留在前列腺的后表面。与筋膜内分离相比,这种方法允许前列腺周围有更大的组织缓冲区,可能是肿瘤学上较安全的方法。
3.Extrafascial dissection(筋膜外分离)
筋膜外分离是在LAF外侧和pPF / SVF后方分离(图9)。在这种情况下,沿前列腺后外侧延伸的NVB被完全切除,同时LAF、PF和pPF/SVF被保留在前列腺。与筋膜内和筋膜间分离相比,这种方法使前列腺周围组织量最大。因此,它是肿瘤学上最安全的分离方法,但可能导致完全的勃起功能障碍。
02 Vesicoprostatic muscle(膀胱前列腺肌)
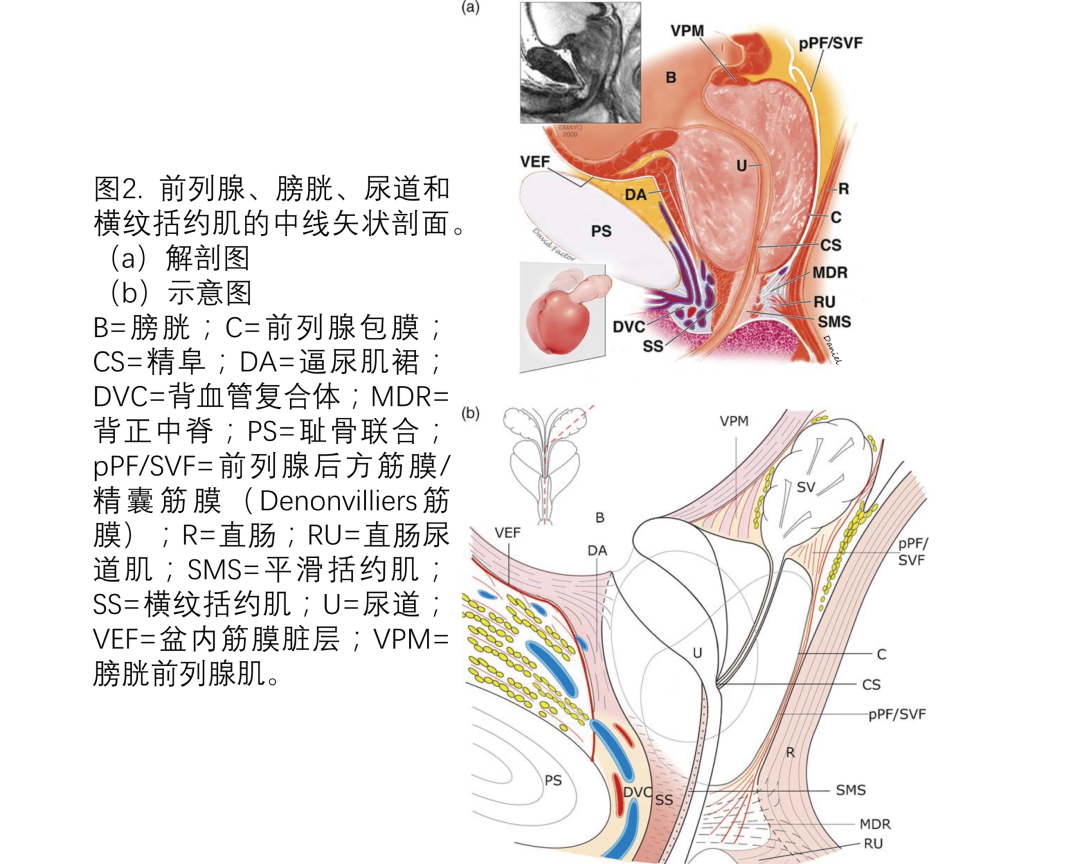
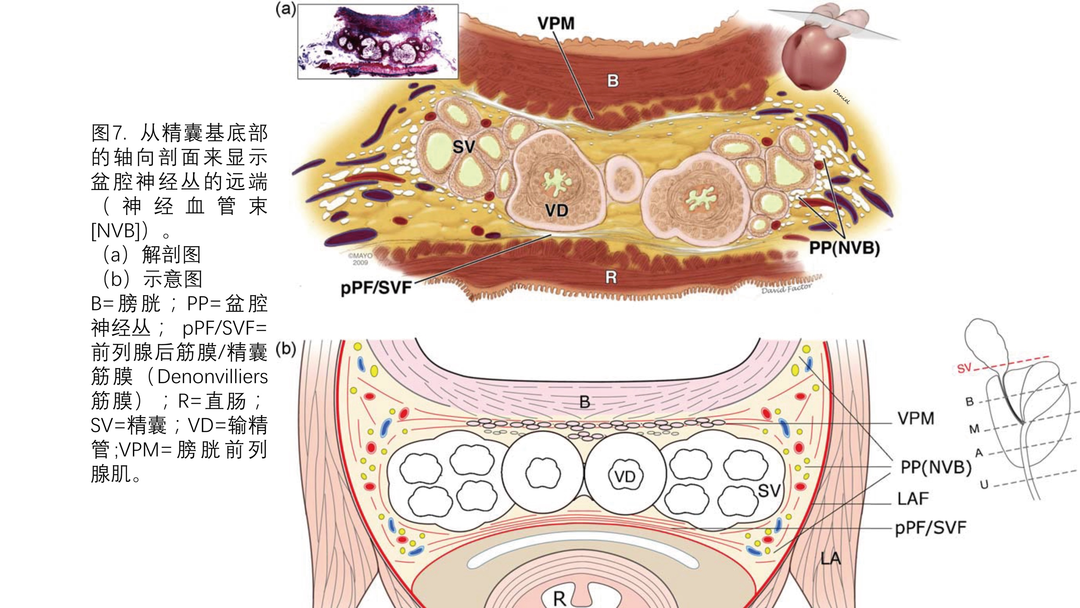
在前列腺后方游离时,膀胱颈后部与精囊和输精管壶腹之间的组织有着重要作用(图2和7)。该组织层被认为含有pPF/SVF的前层。一项研究表明,该组织包含两种不同的组织类型。内层组织直接位于膀胱黏膜下,由起源于外侧纵向逼尿肌的平滑肌纤维组成。这些纤维纵向走行并插入前列腺基底部。该层被认为与腹侧逼尿肌群相对应,被称为膀胱前列腺肌。更靠后方的第二层组织与内层紧密接触,由纤维脂肪组织组成,与膀胱外膜连续。
03 Pelvic floor musculature(盆底肌肉系统)
前盆腔最内层肌肉是肛提肌。在尿道括约肌附近,它被称为尿道提肌、前列腺提肌或耻骨尿道肌,代表了肛提肌的前内侧部分(图1,3,5)。有两份报告将该肌肉的术语定为耻骨会阴肌。报告认为耻骨会阴肌作为肛提肌增厚的部分,由两块源自耻骨的带状肌肉组成,位于前列腺尿道交界处的两侧,在尿道的背侧和肛门直肠交界处的前方附着于会阴体(图3)。相对于肛提肌的其他部分,这部分从侧面邻近的耻骨直肠肌的前方伸出。耻骨会阴肌和耻骨直肠肌的自主收缩将尿道向前、向上牵拉,导致尿道关闭和尿流终止。这些肌肉很可能负责排尿时的主动快-停机制,因此在主动维持尿控方面有着重要作用,在游离前列腺尖部和尿道时,以及吻合膀胱尿道时可能存在损伤的风险。
通常将肛肠交界处与会阴体之间的肌肉结构称为直肠尿道肌,其位于尿道括约肌复合体的远端(>1cm)(图2和3)。该肌肉结构与经会阴根治性前列腺切除术有关,因需要将其切开以进入前列腺尖部。然而一些研究表明,该肌肉与尿道并无接触,这意味着术语“直肠尿道肌”是不恰当的。
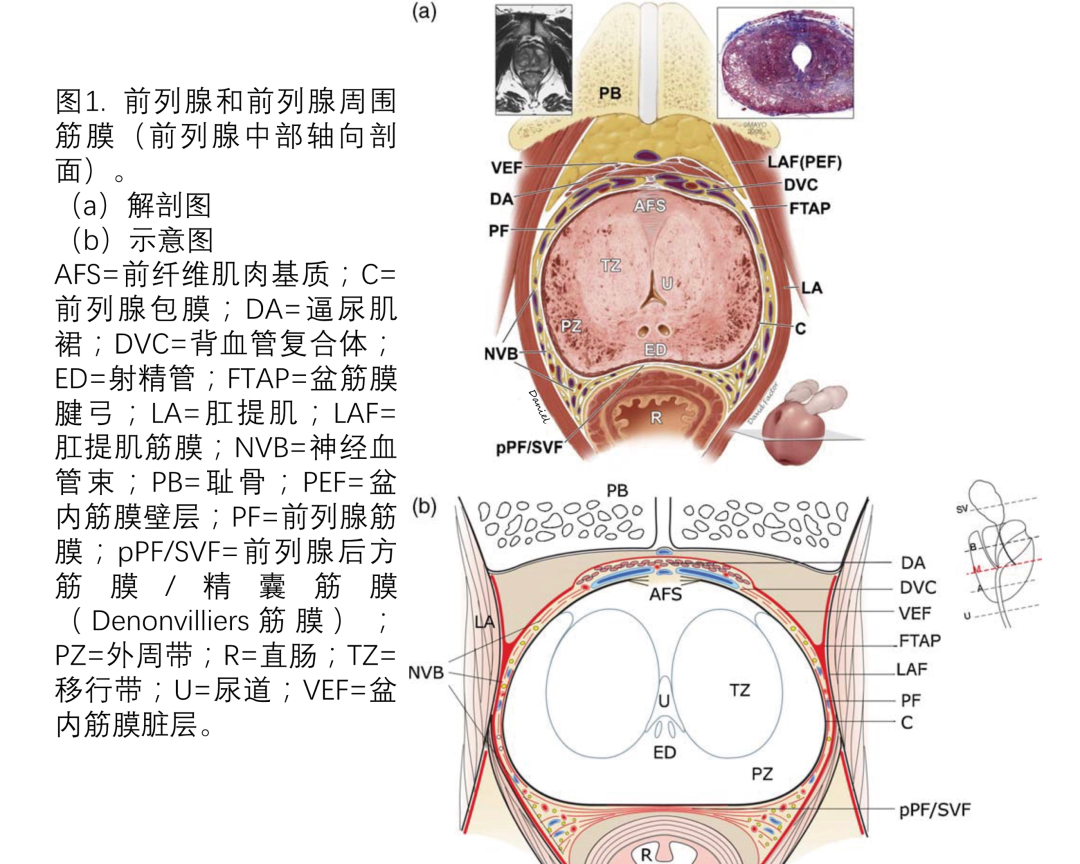
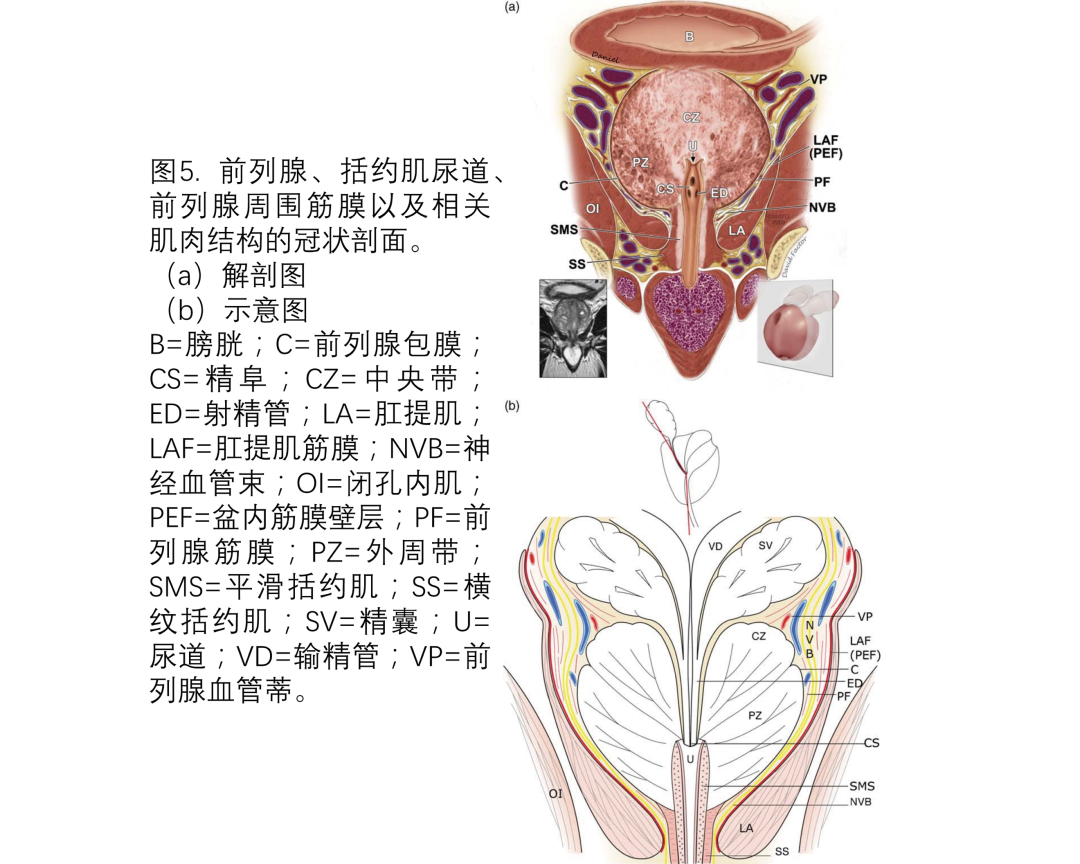
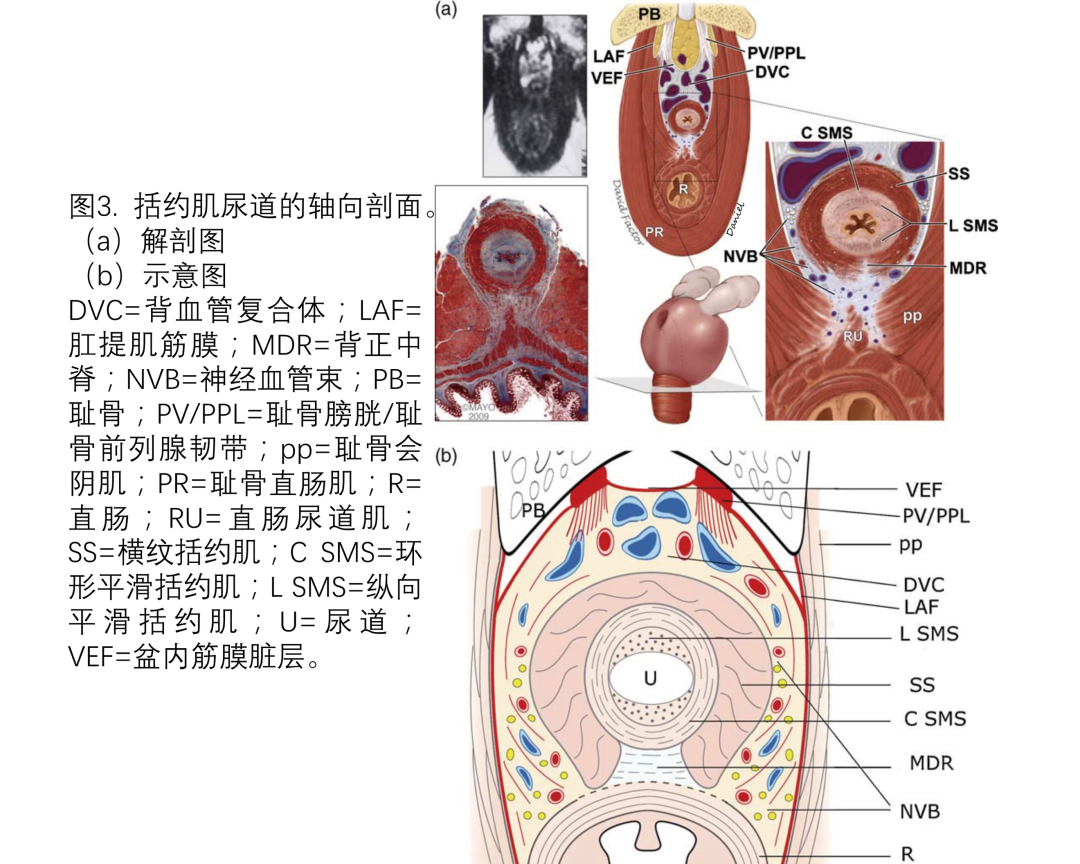
04 External urethral sphincter(尿道外括约肌)
尿道外括约肌复合体主要位于前列腺尖部的远端。它与耻骨会阴肌关系密切但又相互独立,因此单独位于盆底(图2,3,5)。它受盆腔神经丛的自主神经支配,这些自主神经部分与NVB并行,部分来自阴部神经的分支。这些神经纤维在两侧从后外侧进入尿道括约肌,主要在5点钟和7点钟位置,以及3点钟和9点钟位置。前列腺尖部距最近的阴部神经分支进入尿道括约肌的位置为3-13mm。
尿道括约肌和前列腺尖部的后方靠近直肠的前表面(图2和3)。尿道括约肌本身由两种不同类型的肌肉组成(图3)。外层肌由横纹肌纤维构成,外形为垂直的圆柱形至圆锥形,横截面呈马蹄形或Ω形。有人将这部分括约肌命名为“横纹括约肌”。但该肌纤维的走行尚不清楚,可能是水平或垂直的。这种差异可能与尿道腔相对于人体纵轴存在不同轴线,以及组织学切片方式有关。这些肌纤维主要为慢肌纤维,相对于耻骨会阴肌的快肌纤维而言,其在排尿控制方面具有被动功能。横纹括约肌插入前列腺尖部和前表面。括约肌腹侧和腹外侧的肌肉较厚,后外侧的较薄。括约肌的后半圈被背正中脊腱弓中断,背正中脊在括约肌尾侧与会阴中心腱连续,向头侧与pPF/SVF连续。一些作者认为,背正中脊和邻近组织作为括约肌收缩时的支点,使尿道向背侧和尾侧方向运动。这种收缩与耻骨会阴肌的收缩相结合,形成了闭合尿道的双吊索机制。在根治性前列腺切除术中重建这一后方支点可能会改善早期尿控恢复。但尚无确切证据。
尿道括约肌的内层肌完全围绕着尿道,由平滑肌纤维和弹性组织构成。但有人提出该肌肉的形状类似于横纹肌的Ω形。平滑肌层可分为靠外的环形层和靠内的纵向层。靠内的纵向肌层主要位于尿道的前面和后面。但所有的肌层都相互混杂,这表明括约肌的活动是所有肌层联动的结果。
05 Apical prostate shape(前列腺尖部形状)
前列腺尖部的形状可能会有很大变化,直接影响从尖部发出的尿道长度。尖部可能呈环状、双侧对称、单侧不对称、仅前方、仅后方与尿道括约肌重叠,或直接终止于尿道括约肌上方(图11)。Lee等指出,在所有病例中,38%的为环状重叠,25%的为前方重叠,22%的为后方重叠,15%的未重叠。在游离以及横断尖部尿道时应注意——明显的重叠使尿道括约肌长度的保留变得困难。
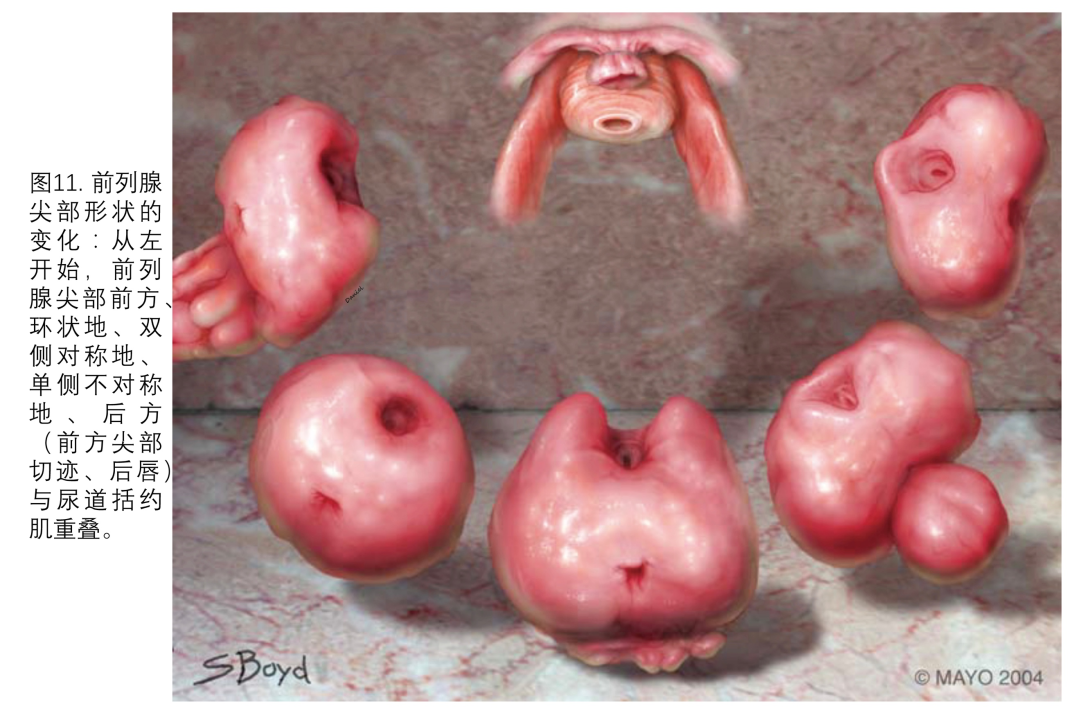
参考文献:(上下滑动阅读)
[1] Roehl KA, Han M, Ramos CG, Antenor JA, Catalona WJ. Cancer progression and survival rates following anatomical radical retropubic prostatectomy in 3,478 consecutive patients: longterm results. J Urol 2004;172:910–4.
[2] Hull GW, Rabbani F, Abbas F,Wheeler TM, KattanMW, Scardino PT. Cancer control with radical prostatectomy alone in 1,000 consecutive patients. J Urol 2002;167:528–34.
[3] Michl UH, Friedrich MG, Graefen M, Haese A, Heinzer H, Huland H. Prediction of postoperative sexual function after nerve sparing radical retropubic prostatectomy. J Urol 2006;176:227–31.
[4] Catalona WJ, Carvalhal GF, Mager DE, Smith DS. Potency, continence and complication rates in 1,870 consecutive radical retropubic prostatectomies. J Urol 1999;162:433–8.
[5] Graefen M, Walz J, Huland H. Open retropubic nerve-sparing radical prostatectomy. Eur Urol 2006;49:38–48.
[6] Majoros A, Bach D, Keszthelyi A, Hamvas A, Romics I. Urinary incontinence and voiding dysfunction after radical retropubic prostatectomy (prospective urodynamic study). Neurourol Urodyn 2006;25:2–7.
[7] Walsh PC, Donker PJ. Impotence following radical prostatectomy: insight into etiology and prevention. J Urol 1982;128:492–7.
[8] Myers RP. Practical surgical anatomy for radical prostatectomy. Urol Clin North Am 2001;28:473–90.
[9] Wimpissinger TF, Tschabitscher M, Feichtinger H, Stackl W. Surgical anatomy of the puboprostatic complex with special reference to radical perineal prostatectomy. BJU Int 2003;92:681–4.
[10] Myers RP. Detrusor apron, associated vascular plexus, and avascular plane: relevance to radical retropubic prostatectomy—anatomic and surgical commentary. Urology 2002;59:472–9.
[11] Santorini GD. De virorum naturalibus [Concerning the male genitalia]. In Baptista Recurti G. Observationes Anatomicae. Venice, Italy; 1724. Chapter XX. p. 202.
[12] Takenaka A, Tewari AK, Leung RA, et al. Preservation of the puboprostatic collar and puboperineoplasty for early recovery of urinary continence after robotic prostatectomy: anatomic basis and preliminary outcomes. Eur Urol 2007;51:433–40, discussion 440.
[13] Walsh PC, Partin AW. Anatomic radical retropubic prostatectomy. In: Wein AJ, Kavoussi LR, Peters CA, Novick AC, Partin AW, eds. Campbell-Walsh urology, Vol 3. Philadelphia, PA: Elsevier Health Sciences; 2006. p. 2956–78.
[14] Stolzenburg J-U, Schwalenberg T, Horn L-C, Neuhaus J, Constantinides C, Liatsikos EN. Anatomical landmarks of radical prostatectomy. Eur Urol 2007;51:629–39.
[15] Steiner MS. The puboprostatic ligament and the male urethral suspensory mechanism: an anatomic study. Urology 1994;44: 530–4.
[16] Presti Jr JC, Schmidt RA, Narayan PA, Carroll PR, Tanagho EA. Pathophysiology of urinary incontinence after radical prostatectomy. J Urol 1990;143:975–8.
[17] Poore RE, McCullough DL, Jarow JP. Puboprostatic ligament sparing improves urinary continence after radical retropubic prostatectomy. Urology 1998;51:67–72.
[18] Deliveliotis C, Protogerou V, Alargof E, Varkarakis J. Radical prostatectomy: bladder neck preservation and puboprostatic ligament sparing—effects on continence and positive margins. Urology 2002;60:855–8.
[19] Burnett AL, Mostwin JL. In situ anatomical study of the male urethral sphincteric complex: relevance to continence preservation following major pelvic surgery. J Urol 1998;160:1301–6.
[20] Buda¨us L, Isbarn H, Schlomm T, et al. Current technique of open intrafascial nerve-sparing retropubic prostatectomy. Eur Urol 2009;56:317–24.
[21] Menon M, Shrivastava A, Kaul S, et al. Vattikuti Institute prostatectomy: contemporary technique and analysis of results. Eur Urol 2007;51:648–58, discussion 657-8.
[22] Tewari AK, Bigelow K, Rao S, et al. Anatomic restoration technique of continence mechanism and preservation of puboprostatic collar: a novel modification to achieve early urinary continence in men undergoing robotic prostatectomy. Urology 2007;69:726–31.
[23] Benoit G, Droupy S, Quillard J, Paradis V, Giuliano F. Supra and infralevator neurovascular pathways to the penile corpora cavernosa.
J Anat 1999;195:605–15.
[24] Takenaka A, Hara R, Soga H, Murakami G, Fujisawa M. A novel technique for approaching the endopelvic fascia in retropubic radical prostatectomy, based on an anatomical study of fixed and fresh cadavers. BJU Int 2005;95:766–71.
[25] Myers RP, Villers A. Anatomic considerations in radical prostatectomy. In: Kirby RS, Partin AW, Feneley M, Parsons JK, eds. Prostate Cancer; Principles and Practice, Vol 1. Abingdon, UK: Taylor & Francis; 2006. p. 701–13.
[26] Magera Jr JS, Inman BA, Slezak JM, Bagniewski SM, Sebo TJ, Myers RP. Increased optical magnification from 2.5to 4.3with technical modification lowers the positive margin rate in open radical retropubic prostatectomy. J Urol 2008;179:130–5.
[27] Polascik TJ, Walsh PC. Radical retropubic prostatectomy: the influence of accessory pudendal arteries on the recovery of sexual function. J Urol 1995;154:150–2.
[28] Droupy S, Hessel A, Benoit G, Blanchet P, Jardin A, Giuliano F. Assessment of the functional role of accessory pudendal arteries in erection by transrectal color Doppler ultrasound. J Urol 1999;162: 1987–91.
[29] Rosen MP, Greenfield AJ, Walker TG, et al. Arteriogenic impotence: findings in 195 impotent men examined with selective internal pudendal angiography. Young Investigator’s Award. Radiology 1990;174:1043–8.
[30] Rogers CG, Trock BP, Walsh PC. Preservation of accessory pudendal arteries during radical retropubic prostatectomy: surgical technique and results. Urology 2004;64:148–51.
[31] Secin FP, Karanikolas N, Touijer AK, Salamanca JI, Vickers AJ, Guillonneau B. Anatomy of accessory pudendal arteries in laparoscopic radical prostatectomy. J Urol 2005;174:523–6, discussion 526.
[32] Mulhall JP, Slovick R, Hotaling J, et al. Erectile dysfunction after radical prostatectomy: hemodynamic profiles and their correlation with the recovery of erectile function. J Urol 2002;167: 1371–5.
[33] Secin FP, Touijer K, Mulhall J, Guillonneau B. Anatomy and preservation of accessory pudendal arteries in laparoscopic radical prostatectomy. Eur Urol 2007;51:1229–35.
[34] Millin T. Retropubic Urinary Surgery. Edinburgh, UK: E & S Livingstone; 1947. p. 46.
[35] Steiner MS. Continence-preserving anatomic radical retropubic prostatectomy. Urology 2000;55:427–35.
[36] Federative Committee on Anatomical Terminology. Terminologia Anatomica: International Anatomical Terminology. Stuttgart, Germany: Thieme; 1998.
[37] Stolzenburg J-U, Rabenalt R, Do M, et al. Intrafascial nerve-sparing endoscopicextraperitoneal radicalprostatectomy.EurUrol2008;53: 931–40.
[38] Savera AT, Kaul S, Badani K, Stark AT, Shah NL, Menon M. Robotic radical prostatectomy with the ‘‘veil of Aphrodite’’ technique: histologic evidence of enhanced nerve sparing. Eur Urol 2006;49: 1065–74, discussion 1073-4.
[39] Kiyoshima K, Yokomizo A, Yoshida T, et al. Anatomical features of periprostatic tissue and its surroundings: a histological analysis of 79 radical retropubic prostatectomy specimens. Jpn J Clin Oncol 2004;34:463–8.
[40] Ayala AG, Ro JY, Babaian R, Troncoso P, Grignon DJ. The prostatic capsule: does it exist? Its importance in the staging and treatment of prostatic carcinoma. Am J Surg Pathol 1989;13:21–7.
[41] Gillitzer R, Thuroff JW, Neisius A, Wollner J, Hampel C. Robotassisted ascending-descending laparoscopic nerve-sparing prostatectomy. BJU Int 2009;104:128–53.
[42] Costello AJ, Brooks M, Cole OJ. Anatomical studies of the neurovascular bundle and cavernosal nerves. BJU Int 2004;94:1071–6.
[43] Kessler TM, Burkhard FC, Studer UE. Nerve-sparing open radical retropubic prostatectomy. Eur Urol 2007;51:90–7.
[44] Tewari A, Peabody JO, Fischer M, et al. An operative and anatomic study to help in nerve sparing during laparoscopic and robotic radical prostatectomy. Eur Urol 2003;43:444–54.
[45] Menon M, Kaul S, Bhandari A, Shrivastava A, Tewari A, Hemal A. Potency following robotic radical prostatectomy: a questionnaire based analysis of outcomes after conventional nerve sparing and prostatic fascia sparing techniques. J Urol 2005;174:2291–6, discussion 2296.
[46] Secin FP, Serio A, Bianco Jr FJ, et al. Preoperative and intraoperative risk factors for side-specific positive surgical margins in laparoscopic radical prostatectomy for prostate cancer. Eur Urol 2007;51:764–71.
[47] Nielsen ME, Schaeffer EM, Marschke P, Walsh PC. High anterior release of the levator fascia improves sexual function following open radical retropubic prostatectomy. J Urol 2008;180:2557–64, discussion 2564.
[48] Kourambas J, Angus DG, Hosking P, Chou ST. A histological study of Denonvilliers’ fascia and its relationship to the neurovascular bundle. Br J Urol 1998;82:408–10.
[49] Montorsi F, Salonia A, Suardi N, et al. Improving the preservation of the urethral sphincter and neurovascular bundles during open radical retropubic prostatectomy. Eur Urol 2005;48: 938–45.
[50] Hong H, Koch MO, Foster RS, et al. Anatomic distribution of periprostatic adipose tissue: a mapping study of 100 radical prostatectomy specimens. Cancer 2003;97:1639–43.
[51] Lindsey I, Guy RJ, Warren BF, Mortensen NJ. Anatomy of Denonvilliers’ fascia and pelvic nerves, impotence, and implications for the colorectal surgeon. Br J Surg 2000;87:1288–99.
[52] Tobin C, Benjamin J. Anatomical and surgical restudy of the Denonvilliers’ fascia. Surg Gynecol Obstet 1945;80:373–88.
[53] Huland H, Noldus J. An easy and safe approach to separating Denonvilliers’ fascia from rectum during radical retropubic prostatectomy. J Urol 1999;161:1533–4.
[54] Church JM, Raudkivi PJ, Hill GL. The surgical anatomy of the rectum—a review with particular relevance to the hazards of rectal mobilisation. Int J Colorectal Dis 1987;2:158–66.
[55] Silver PH. The role of the peritoneum in the formation of the septum recto-vesicale. J Anat 1956;90:538–46.
[56] Villers A, McNeal JE, Freiha FS, Boccon-Gibod L, Stamey TA. Invasion of Denonvilliers’ fascia in radical prostatectomy specimens. J Urol 1993;149:793–8.
[57] Villers A, Piechaud T. Surgical anatomy of the prostate for radical prostatectomy. In: John H, Wiklund P, eds. Robotic Urology. New York, NY: Springer Berlin Heidelberg; 2008.
[58] van Ophoven A, Roth S. The anatomy and embryological origins of the fascia of Denonvilliers: a medico-historical debate. J Urol 1997;157:3–9.
[59] Lepor H, Gregerman M, Crosby R, Mostofi FK, Walsh PC. Precise localization of the autonomic nerves from the pelvic plexus to the corpora cavernosa: a detailed anatomical study of the adult male pelvis. J Urol 1985;133:207–12.
[60] McNeal JE. Normal histology of the prostate. Am J Surg Pathol 1988;12:619–33.
[61] Kinugasa Y, Murakami G, Uchimoto K, Takenaka A, Yajima T, Sugihara K. Operating behind Denonvilliers’ fascia for reliable preservation of urogenital autonomic nerves in total mesorectal excision: a histologic study using cadaveric specimens, including a surgical experiment using fresh cadaveric models. Dis Colon Rectum 2006;49:1024–32.
[62] McNeal JE. The prostate and prostatic urethra: a morphologic synthesis. J Urol 1972;107:1008–16.
[63] Epstein JI. Pathologic assessment of the surgical specimen. Urol Clin North Am 2001;28:567–94.
[64] Mauroy B, Demondion X, Drizenko A, et al. The inferior hypogastric plexus (pelvic plexus): its importance in neural preservation techniques. Surg Radiol Anat 2003;25:6–15.
[65] Baader B, Herrmann M. Topography of the pelvic autonomic nervous system and its potential impact on surgical intervention in the pelvis. Clin Anat 2003;16:119–30.
[66] Tewari A, Takenaka A, Mtui E, et al. The proximal neurovascular plate and the tri-zonal neural architecture around the prostate gland: importance in the athermal robotic technique of nervesparing prostatectomy. BJU Int 2006;98:314–23.
[67] Mu¨ ller J. U¨ ber die organischen Nerven der erectilen ma¨nnlichen Geschlechtsorgane des Menschen und der Sa¨ugethiere [Concerning the autonomic nerves of the male erectile genital organs of man and mammals]. Berlin, Germany: F. Du¨mmler; 1836.
[68] Lunacek A, Schwentner C, Fritsch H, Bartsch G, Strasser H. Anatomical radical retropubic prostatectomy: ‘curtain dissection’ of the neurovascular bundle. BJU Int 2005;95:1226–31.
[69] Schlegel PN, Walsh PC. Neuroanatomical approach to radical cystoprostatectomy with preservation of sexual function. J Urol 1987;138:1402–6.
[70] Hollabaugh Jr RS, Dmochowski RR, Kneib TG, Steiner MS. Preservation
of putative continence nerves during radical retropubic prostatectomy leads to more rapid return of urinary continence. Urology 1998;51:960–7.
[71] John H, Hauri D. Seminal vesicle-sparing radical prostatectomy: a novel concept to restore early urinary continence. Urology 2000;55:820–4.
[72] Jepsen JV, Bruskewitz RC. Should the seminal vesicles be resected during radical prostatectomy? Urology 1998;51:12–8.
[73] Takenaka A, Murakami G, Soga H, Han SH, Arai Y, Fujisawa M. Anatomical analysis of the neurovascular bundle supplying penile cavernous tissue to ensure a reliable nerve graft after radical prostatectomy. J Urol 2004;172:1032–5.
[74] Takenaka A, Murakami G, Matsubara A, Han SH, Fujisawa M. Variation in course of cavernous nerve with special reference to details of topographic relationships near prostatic apex: histologic study using male cadavers. Urology 2005;65:136–42.
[75] Walsh PC, Marschke P, Ricker D, Burnett AL. Use of intraoperative video documentation to improve sexual function after radical retropubic prostatectomy. Urology 2000;55:62–7.
[76] Ganzer R, Blana A, Stolzenburg JU, et al. Nerve quantification and computerized planimetry to evaluate periprostatic nerve distribution— does size matter? Urology 2009;74:398–403.
[77] Sievert K-D, Hennenlotter J, Laible I, et al. The periprostatic autonomic nerves—bundle or layer? Eur Urol 2008;54:1109–17.
[78] Eichelberg C, Erbersdobler A, Michl U, et al. Nerve distribution along the prostatic capsule. Eur Urol 2007;51:105–11, discussion 110–1.
[79] Ganzer R, Blana A, Gaumann A, et al. Topographical anatomy of periprostatic and capsular nerves: quantification and computerised planimetry. Eur Urol 2008;54:353–61.
[80] Kaiho Y, Nakagawa H, Saito H, et al. Nerves at the ventral prostatic capsule contribute to erectile function: initial electrophysiological assessment in humans. Eur Urol 2009;55:148–55.
[81] Rassweiler J. Intrafascial nerve-sparing laparoscopic radical prostatectomy: do we really preserve relevant nerve-fibres? Eur Urol 2006;49:955–7.
[82] Paick JS, Donatucci CF, Lue TF. Anatomy of cavernous nerves distal to prostate: microdissection study in adult male cadavers. Urology 1993;42:145–9.
[83] Zorn KC, Gofrit ON, Orvieto MA, Mikhail AA, Zagaja GP, Shalhav AL
Robotic-assisted laparoscopic prostatectomy: functional and pathologic outcomes with interfascial nerve preservation. Eur Urol 2007;51:755–63, discussion 763.
[84] Barre´ C. Open radical retropubic prostatectomy. Eur Urol 2007;52: 71–80.
[85] Secin FP, Karanikolas N, Gopalan A, et al. The anterior layer of Denonvilliers’ fascia: a common misconception in the laparoscopic prostatectomy literature. J Urol 2007;177:521–5.
[86] Guillonneau B, Vallancien G. Laparoscopic radical prostatectomy: the Montsouris technique. J Urol 2000;163:1643–9.
[87] Dorschner W, Stolzenburg JU, Dieterich F. A new theory of micturition and urinary continence based on histomorphological studies. 2. The musculus sphincter vesicae: continence or sexual function? Urol Int 1994;52:154–8.
[88] Krause W. Muskeln am Beckenausgange. Hannover, Germany: Han’sche Buchhandlung; 1879.
[89] Meckel JF. Handbuch der menschlichen Anatomie. Halle, Germany: Hallesches Weisenhaus; 1820.
[90] Myers RP, Cahill DR, Kay PA, et al. Puboperineales: muscular boundaries of the male urogenital hiatus in 3D from magnetic resonance imaging. J Urol 2000;164:1412–5.
[91] Cambio AJ, Evans CP. Minimising postoperative incontinence following radical prostatectomy: considerations and evidence. Eur Urol 2006;50:903–13, discussion 913.
[92] Brooks JD, Chao WM, Kerr J. Male pelvic anatomy reconstructed from the visible human data set. J Urol 1998;159:868–72.
[93] Gosling JA, Dixon JS, Humpherson JR. Functional anatomy of the urinary tract. Baltimore, MD: University Park Press; 1982.
[94] Porzionato A, Macchi V, Gardi M, Parenti A, De Caro R. Histotopographic study of the rectourethralis muscle. Clin Anat 2005;18: 510–7.
[95] Sebe P, Oswald J, Fritsch H, Aigner F, Bartsch G, Radmayr C. An embryological study of fetal development of the rectourethralis muscle—does it really exist? J Urol 2005;173:583–6.
[96] Soga H, Takenaka A, Murakami G, Fujisawa M. Topographical relationship between urethral rhabdosphincter and rectourethralis muscle: a better understanding of the apical dissection and the posterior stitches in radical prostatectomy. Int J Urol 2008;15: 729–32.
[97] Dorschner W, Biesold M, Schmidt F, Stolzenburg JU. The dispute
about the external sphincter and the urogenital diaphragm. J Urol 1999;162:1942–5.
[98] Akita K, Sakamoto H, Sato T. Origins and courses of the nervous branches to themale urethral sphincter. Surg Radiol Anat 2003;25: 387–92.
[99] Strasser H, Bartsch G. Anatomy and innervation of the rhabdosphincter of the male urethra. Semin Urol Oncol 2000;18:2–8.
[100] Steiner MS. Anatomic basis for the continence-preserving radical retropubic prostatectomy. Semin Urol Oncol 2000;18:9–18.
[101] Tanagho EA, Schmidt RA, de Araujo CG. Urinary striated sphincter: what is its nerve supply? Urology 1982;20:415–7.
[102] Vernet G. Innervation of the posterior urethra and bladder neck [in French]. J Urol Nephrol (Paris) 1974;80:183–9.
[103] Karam I, Droupy S, Abd-Alsamad I, et al. The precise location and nature of the nerves to the male human urethra: histological and immunohistochemical studies with three-dimensional reconstruction. Eur Urol 2005;48:858–64.
[104] Narayan P, Konety B, Aslam K, Aboseif S, Blumenfeld W, Tanagho E.
Neuroanatomy of the external urethral sphincter: implications for urinary continence preservation during radical prostate surgery. J Urol 1995;153:337–41.
[105] Dorschner W, Stolzenburg JU, Neuhaus J. Anatomic principles of urinary incontinence [in German]. Urologe A 2001;40:223–33.
[106] Stolzenburg JU, Schwalenberg T, Do M, et al. Is the male dog comparable to human? A histological study of the muscle systems of the lower urinary tract. Anat Histol Embryol 2002;31:198–205.
[107] Strasser H, Klima G, Poisel S, Horninger W, Bartsch G. Anatomy and innervation of the rhabdosphincter of the male urethra. Prostate 1996;28:24–31.
[108] Oelrich TM. The urethral sphincter muscle in the male. Am J Anat 1980;158:229–46.
[109] Gosling JA, Dixon JS, Critchley HO, Thompson SA. A comparative study of the human external sphincter and periurethral levator ani muscles. Br J Urol 1981;53:35–41.
[110] Schroder HD, Reske-Nielsen E. Fiber types in the striated urethral and anal sphincters. Acta Neuropathol 1983;60:278–82.
[111] Koyanagi T. Studies on the sphincteric system located distally in the urethra: the external urethral sphincter revisited. J Urol 1980;124:400–6.
[112] Rocco F, Carmignani L, Acquati P, et al. Early continence recovery after open radical prostatectomy with restoration of the posterior aspect of the rhabdosphincter. Eur Urol 2007;52:376–83.
[113] Rocco B, Gregori A, Stener S, et al. Posterior reconstruction of the rhabdosphincter allows a rapid recovery of continence after transperitoneal videolaparoscopic radical prostatectomy. Eur Urol 2007;51:996–1003.
[114] Rocco F, Carmignani L, Acquati P, et al. Restoration of posterior aspect of rhabdosphincter shortens continence time after radical retropubic prostatectomy. J Urol 2006;175:2201–6.
[115] Menon M, Muhletaler F, Campos M, Peabody JO. Assessment of early continence after reconstruction of the periprostatic tissues in patients undergoing computer assisted (robotic) prostatectomy: results of a 2 group parallel randomized controlled trial. J Urol 2008;180:1018–23.
[116] Rocco B, Rocco F. Re: Assessment of early continence after reconstruction of the periprostatic tissues in patients undergoing computer assisted (robotic) prostatectomy: results of a 2 group parallel randomized controlled trial: M. Menon, F. Muhletaler, M. Campos and J. O. Peabody J Urol 2008;180:1018–23; J Urol 2009;181:1500–1; author reply 1501.
[117] Myers RP. Male urethral sphincteric anatomy and radical prostatectomy. Urol Clin North Am 1991;18:211–27.
[118] Lee SE, Byun SS, Lee HJ, et al. Impact of variations in prostatic apex shape on early recovery of urinary continence after radical retropubic prostatectomy. Urology 2006;68:137–41.
译者简介

王冬
医学硕士,主治医师。现就职于陕西中医药大学附属医院。陕西省中西医结合学会泌尿外科专委会、男科专委会委员。在西安交通大学第二附属医院学习泌尿外科内腔镜技术。在中山大学附属第六医院学习层面外科学相关理论及技术。在北京大学第一医院完成泌尿外科及男科专科医师培训。
科普专栏作者,泌尿外科医生学习联盟通讯编委。在社交媒体撰写专业文章10余篇,总UV量超过10万人次。
编辑:张桂芳
审核:王欣
终审:郭涛