
【探泌】World J Uro:同期经尿道膀胱肿瘤切除和前列腺切除患者的肿瘤学安全性和生活质量——一项随机对照试验结果

导语
为贯彻落实中华医学会泌尿外科学分会“顶天立地”发展规划,加强国内外学术交流,促进我国泌尿外科事业更好更快发展,学习联盟特推出“探泌”栏目。本栏目秉承“专业,公益,共享,共进”原则,旨在传播国外学科发展资讯,搭建学术交流平台,更好地为我国广大泌尿外科同道服务。
膀胱肿瘤和前列腺增生是泌尿外科的常见疾病,发病率呈逐年增高趋势。对于上述两种病变(肌层浸润性膀胱癌除外),经尿道切除已成为首选手术方案,特别是在激光、剜除等先进设备、术式得到应用以后。但临床医师面对的问题往往更加复杂、棘手,比如这两种良恶性质不同的病变同时发生时,是同期切除还是分期切除?一直是临床上争议的话题。对此,发表于World J Uro杂志题为《Oncological safety and quality of life in men undergoing simultaneous transurethral resection of bladder tumor and prostate: results from a randomized controlled trial》[1]的文章对同期经尿道膀胱肿瘤切除和前列腺切除患者的肿瘤学安全性与生活质量作了研究。
【Abstract】
PURPOSE: To assess oncological safety and quality of life (QL) of men undergoing simultaneous transurethral resection of bladder tumor (TURBT) and transurethral resection of the prostate (TURP) for symptomatic benign prostatic hyperplasia (BPH).
目的:评估同期接受经尿道膀胱肿瘤和前列腺切除患者的肿瘤学安全性与生活质量。
METHODS: Ninety-five men with a new diagnosis of bladder cancer (BC) and symptomatic BPH were randomized to receive TURBT + tamsulosin (Group 1) or TURBT + TURP (Group 2). Inclusion criteria were age ≤ 75 years, first diagnosis of BC up to 4 cm, and prostate volume ≤ 80 ml. All patients were evaluated preoperatively with digital rectal examination, PSA, maximal urine flow rate (Qmax), and International Prostate Symptom Score (IPSS). IPSS and Qmax were repeated at 1-year follow-up. QL was evaluated at 1 year using a modified version of the self-report bladder cancer subscale of the Functional Assessment of Cancer Therapy.
方法:新确诊膀胱肿瘤合并有症状的BPH患者95例,随机分为TURBt+坦索罗辛组(组1)和TURBt+TURP组(组2)。纳入标准:年龄≤ 75岁,首次确诊膀胱肿瘤(≤4.0cm),前列腺体积≤ 80 ml。全部患者均在术前接受经直肠指诊及PSA、Qmax、IPSS测定,并在术后随访至1年时重复评估Qmax和IPSS。术后1年生活质量评分(QL)评估采用改良版自我报告式的膀胱肿瘤评分表(源自Functional Assessment of Cancer Therapy—癌症疗法功能评价表)。
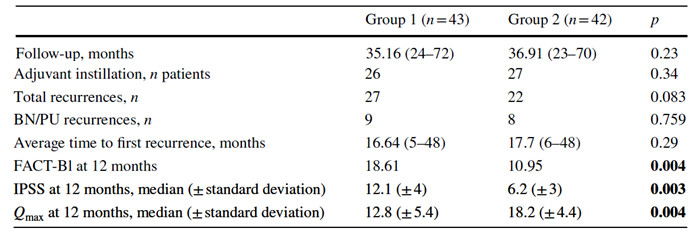
RESULTS: Eighty-five men completed the study (43 in Group 1 and 42 in Group 2). Adjuvant instillation therapy was given to 26 patients in Group 1 and to 27 in Group 2. Average time to the first recurrence was 16.64 months in Group 1 and 17.7 in Group 2. Total recurrences were 27 in Group 1 and 22 in Group 2. Bladder neck/prostatic urethra recurrences were 9 in Group 1 vs. 8 in Group 2. QL, IPSS, and Qmax 12 months after surgery were better in Group 2.
结果:共有85例患者完成了该研究(其中组1为43例、组2为42例)。组1和组2各有26例和27例接受了辅助性膀胱灌注治疗。组1和组2的首次复发平均时间分别为16.64个月和17.7个月。组1和组2的复发例数分别为27例和22例。膀胱颈部/前列腺部尿道的复发例数在组1和组2分别为9例和8例。组2的QL、IPSS和Qmax三项指标改善情况好于组1。
CONCLUSION: Concomitant TURBT and TURP appear to be oncologically safe procedures in terms of total and prostatic urethra recurrence, and improve QL in men with BC who require surgery for symptomatic BPH.
结论:从前列腺部尿道的术后肿瘤复发率方面分析,同期进行TURBt和TURP在肿瘤学方面似乎是(appear to be)安全的, 而且能够提高那些合并需要手术治疗BPH的膀胱肿瘤患者的生活质量。
译者述评
近年来,前列腺增生同时合并膀胱肿瘤的病例有逐渐增加的趋势,而且多数为非肌层浸润性膀胱癌。很多学者认为前列腺增生所致膀胱出口梗阻与膀胱肿瘤的发生有一定关系[2,3]。对此,临床医生常面临两难困境,究竟是同期还是分期处理前列腺增生和膀胱肿瘤?同期处理,有导致膀胱肿瘤细胞播散种植于膀胱颈部和前列腺部尿道的风险;分期处理,则有延误膀胱肿瘤的治疗,或无法尽快解除下尿路梗阻的风险。早在开放手术时代,就已存在类似争议。当时有学者发现,同期手术后高达21.7%的复发性肿瘤位于膀胱颈部[4]。时至今日,争论仍在继续。针对本文,Tsivian等指出“关于同期进行TURBt和TURP的讨论目前尚无明确结论,但该项研究的作者再次向我们展示了这种方法的安全性,我们也乐于分享他们的经验。切除膀胱肿瘤的同时进行TURP,无疑将有助于提高患者的生活质量,从而避免再次手术,并且可能更便于术后的膀胱灌注化疗。上述所提及的问题,有必要慎重权衡利弊并且与患者充分讨论”[5]。我们将在文末附上该篇述评,供同道们继续研读。
与过去不同,经尿道手术方法和医患关系均有了巨大变化。医患关系是个复杂的医学和社会问题,对中国医生而言更是如此,进行医疗决策必须慎而又慎。因此,分期处理的方案似乎更稳妥一些。除了肿瘤学风险外,同期手术后患者一般都会接受膀胱灌注化疗,而前列腺部尿道创面至少是灌注化疗期间膀胱尿道刺激症状的一个高度相关因素,也将影响到患者术后的生活质量。
【参考文献】
1. Dellabella M, Branchi A, Gasparri L, et al. Oncological safety and quality of life in men undergoing simultaneous transurethral resection of bladder tumor and prostate: results from a randomized controlled trial. World J Uro, 2018; 36(10):1629-1634
2. Xiaoyu Dai, Xiangming Fang, Ying Ma, et al. Benign Prostatic Hyperplasia and the Risk of Prostate Cancer and Bladder Cancer: A Meta-Analysis of Observational Studies. Medicine (Baltimore), 2016; 95(18): e3493
3. Alyaev YG, Pshikhachev AM, Perekalina AN. The risk of bladder cancer in patients with prostatic hyperplasia and strategies to manage this combination. Urologiia, 2016; Nov(5): 115-118 [Article in Russian].
4. Golomb J, Gorelik U, Keler T, et al. Incidence and pattern of bladder tumor recurrence following combined suprapubic prostatectomy and excision of a bladder tumor. Eur Urol. 1989; 16(2):86-88
5. Matvey Tsivian, Alexander Tsivian. Challenging the dogma of simultaneous resection of bladder tumor and benign prostate. Translational Andrology and Urology, 2018; 7(s6): s756-s757
责任编辑:榭小仙
审核校对:刘碧君 张广涛