
排尿踌躇、有残余尿,是膀胱出了问题?
作者讲解视频请下方扫码观看

膀胱活动低下症(underactive bladder,UAB)是下尿路功能障碍的一种常见类型,也是近年来尿控领域出现的新名词和研究热点。
目前由于UAB缺乏公认定义、无统一的诊断标准和有效的治疗方法。
人们对其重视程度不够,基础与临床研究很不充分许多患者因UAB导致治疗失败、引发医患纠纷,为下尿路功能障碍的诊治带来了许多严重问题。
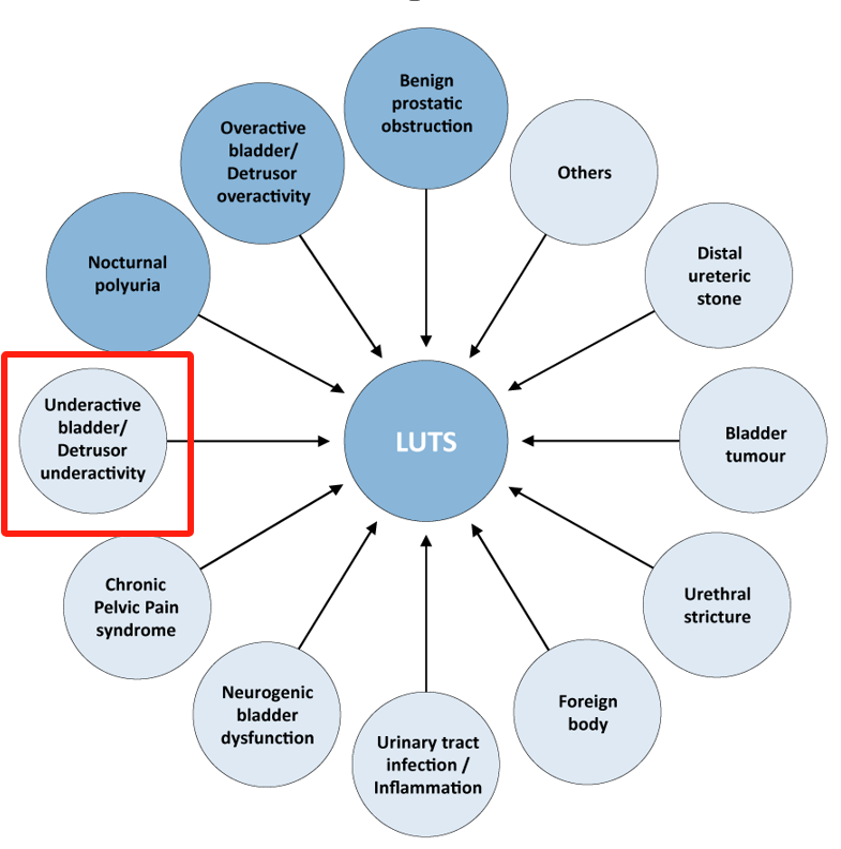
良性前列腺增生(benign prostatic hyperplasia,BPH)合并UAB患者 女性压力性尿失禁(stress urinary incontinence,SUI)合并UAB患者 逼尿肌反射亢进伴收缩力受损(detrusor hyperactivity with impaired contractility,DHIC)患者的治疗策略问题 ………
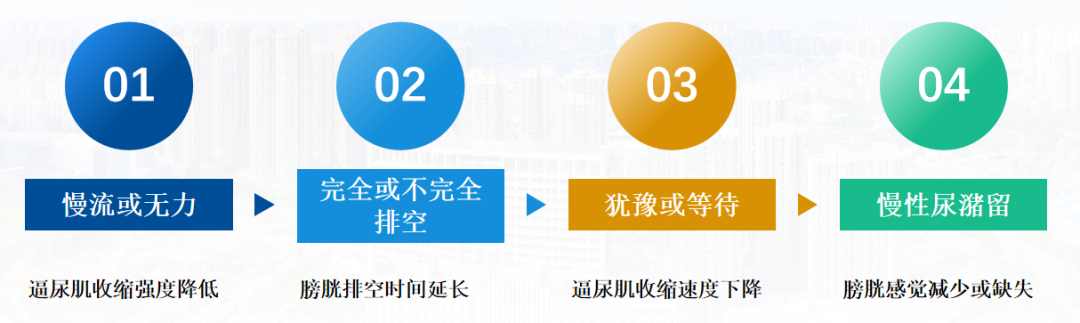
UAB是由各种原因引起的症候群,包括排尿踌躇、排尿费力、排尿困难、尿流缓慢、间断排尿、排尿滴沥、膀胱排空时间延长和/或膀胱排空不全。
逼尿肌活动低下(DU):2002国际尿控协会定义逼尿肌收缩强度和(或)收缩持续时间的减少,导致延长膀胱排空时间和/或在排尿时段内膀胱未能完全排空。
逼尿肌无收缩(AcD):AcD意味着在排尿期间没有逼尿肌的收缩,AcD是DU进展的极端。
逼尿肌反射亢进伴收缩力受损(DHIC):指充盈阶段逼尿肌过度活动(DO)和排尿阶段逼尿肌收缩力低下(DU)。
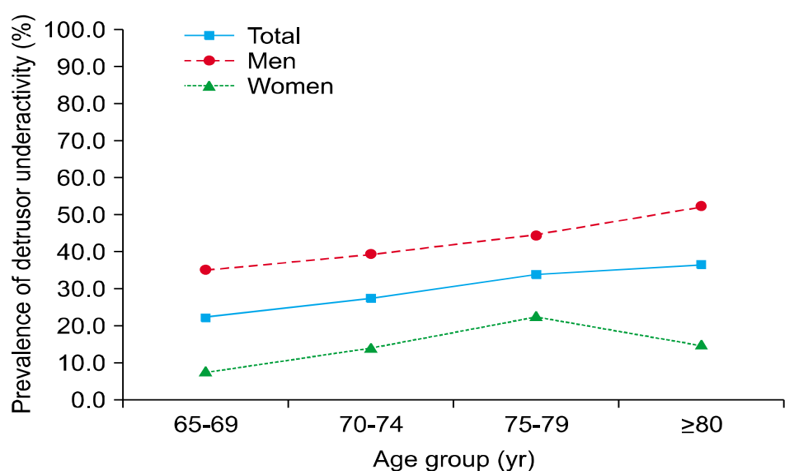
2012年,韩国首尔国立大学邦当医院对1817例患者进行回顾性研究:65岁以上人群UAB发生率接近30%,男性发病率更高。
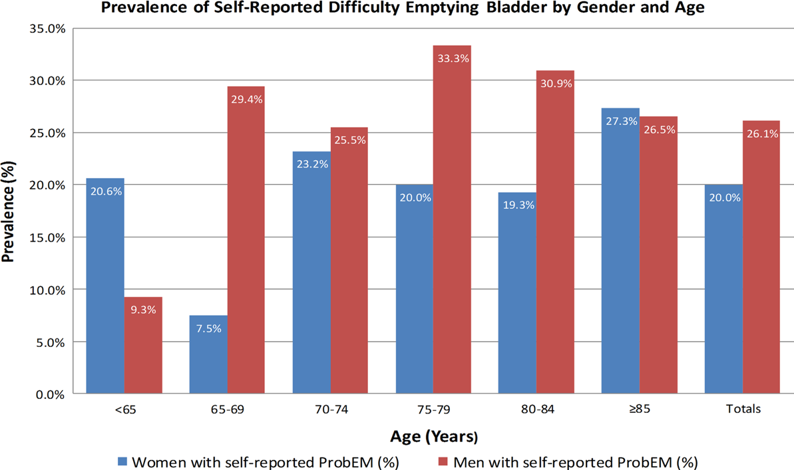
2014年,美国国家老龄化研究所联合美国麻省大学医学院和奥克兰大学威廉·博蒙特医学院对UAB的发病率进行了现况调查研究:65岁以上男性UAB发病率达30%。
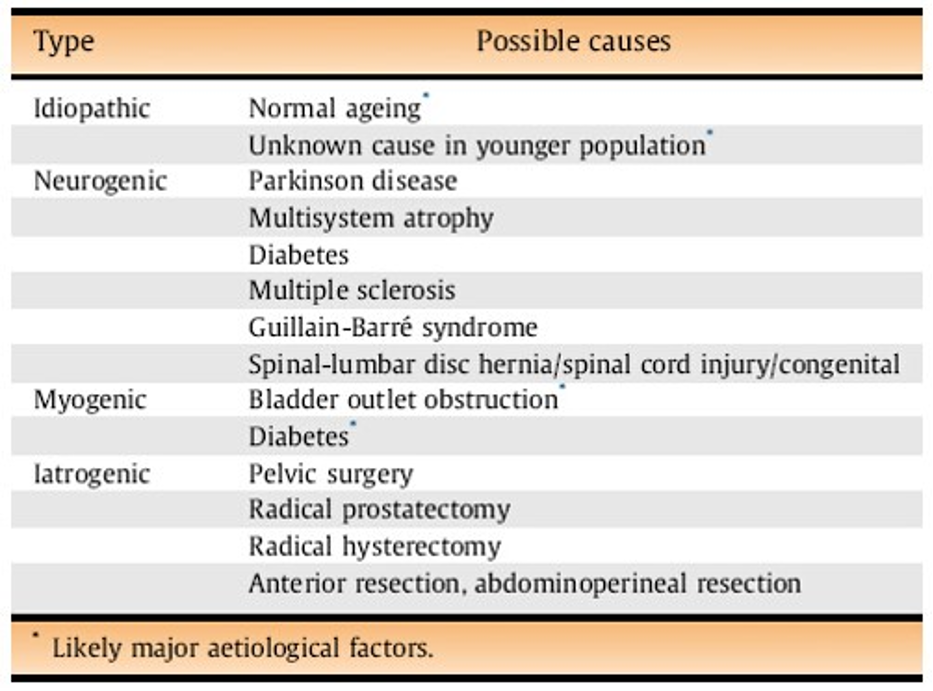
特发性UAB:年龄相关或其他不明原因所致的逼尿肌收缩力下降。
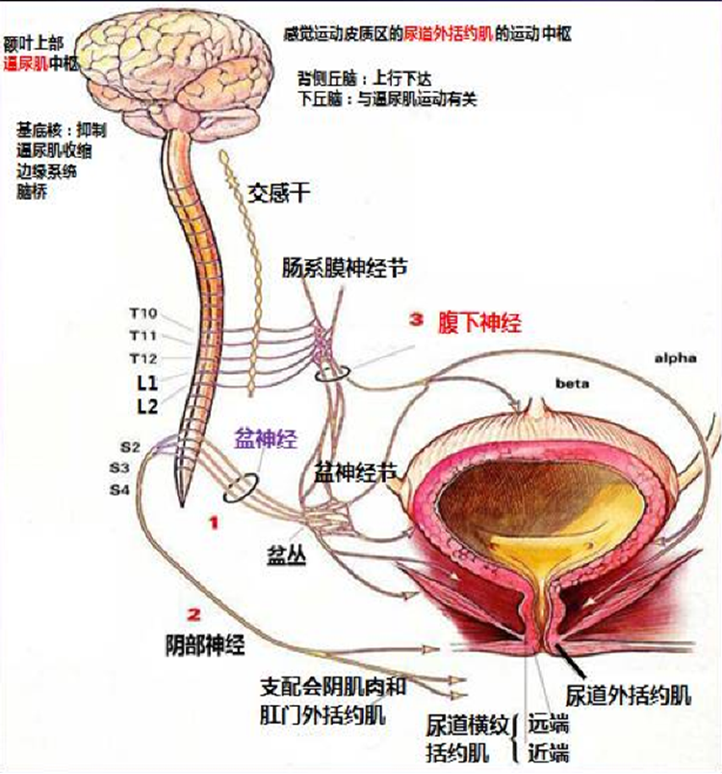
神经源性UAB:排尿反射的中枢及外周神经系统控制影响着感觉、整合和输出过程中的关键环节,其中任何环节功能障碍均可能导致UAB。
肌源性UAB:由于逼尿肌细胞的兴奋-收缩耦合机制改变而导致膀胱自主活动降低。
“弱”“短”“缓”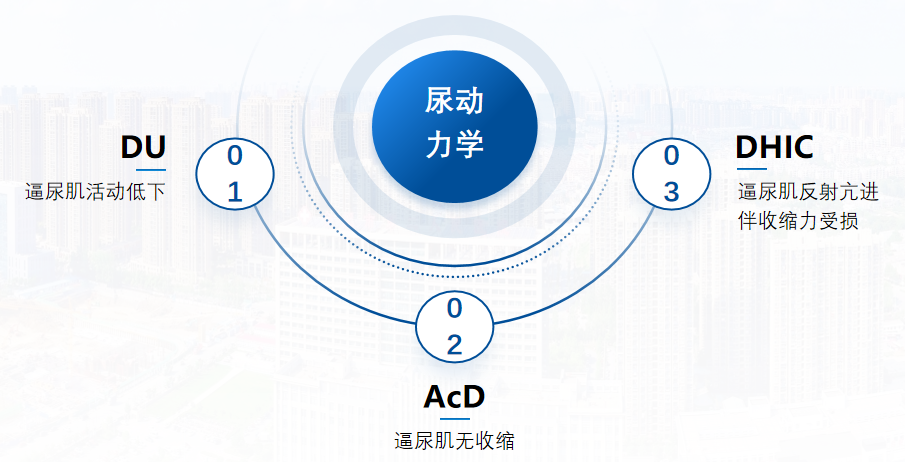
诊断——侵入性压力-流率研究
(pressure-flow study, PFS)
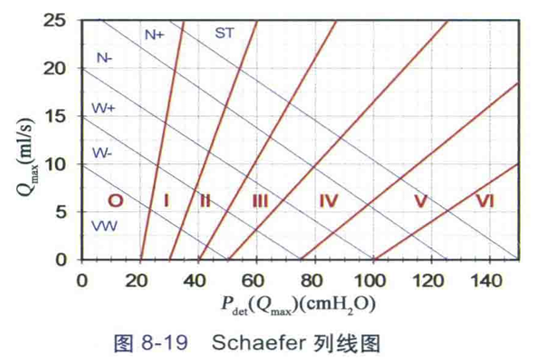
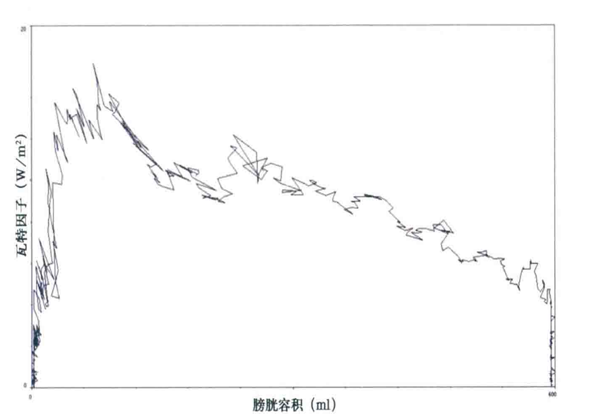
WFmax≤7 W/m2用于诊断DU
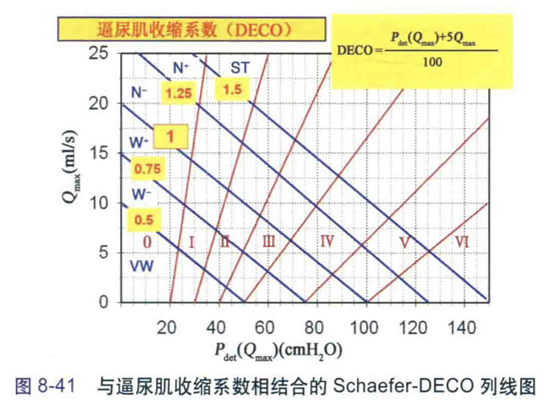
DECO<1被认为是逼尿肌收缩力减弱
女性的诊断尤其困难,因为她们可以通过放松盆底来排尿,也就是说,在压力-流量研究中没有检测到逼尿肌收缩,也没有增加腹压。
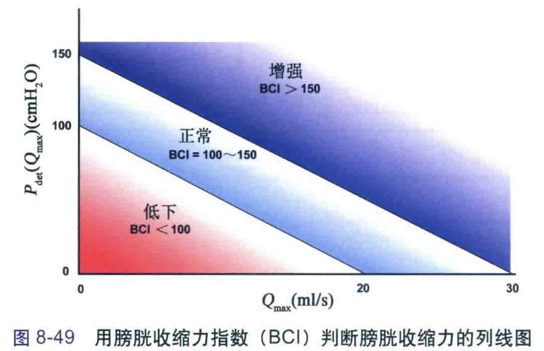
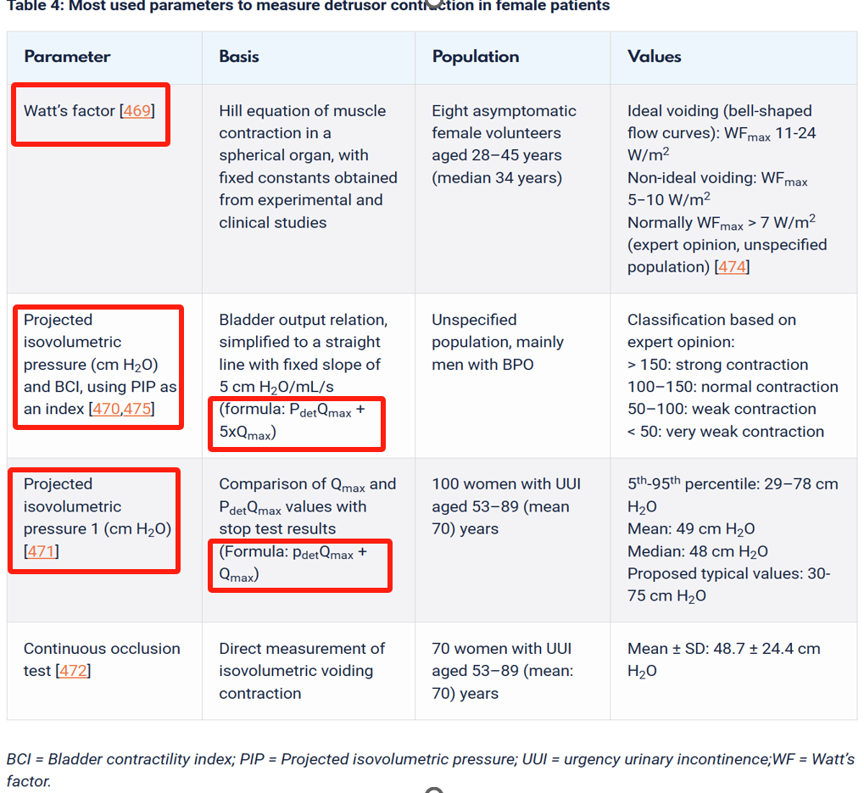
基于Qmax和PdetQmax的cut-off值,可能还结合PVR和BVE的cut-off值。
间歇性导管插入术(IC) 膀胱外压迫(Credé method) 腹压排尿(abdominal straining) 诱发反射性排尿(triggered reflex voiding) 生物反馈盆底肌放松训练(Pelvic floor muscle relaxation training with biofeedback)
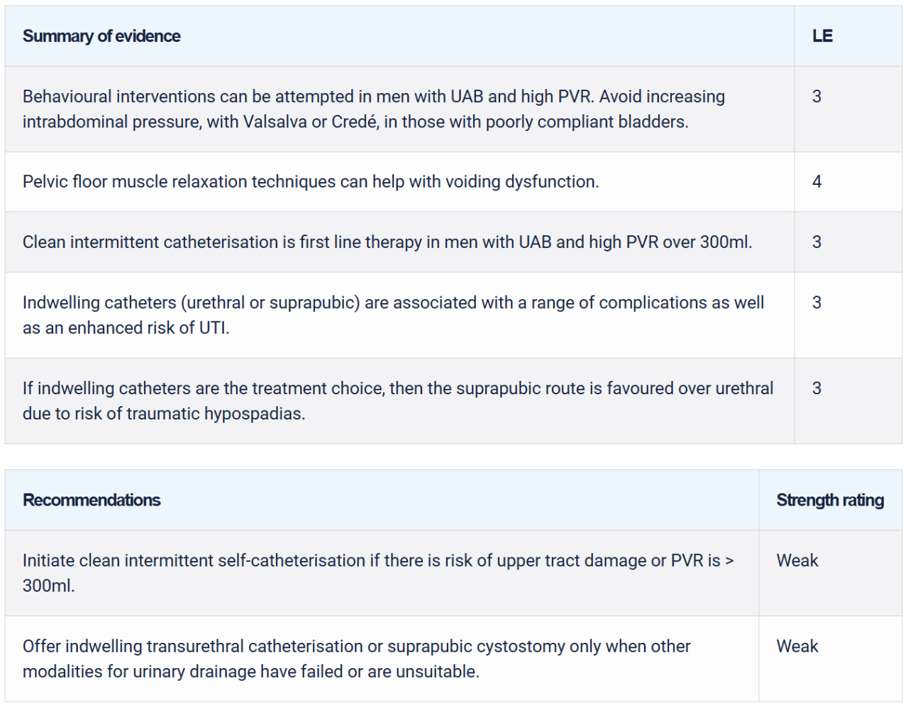
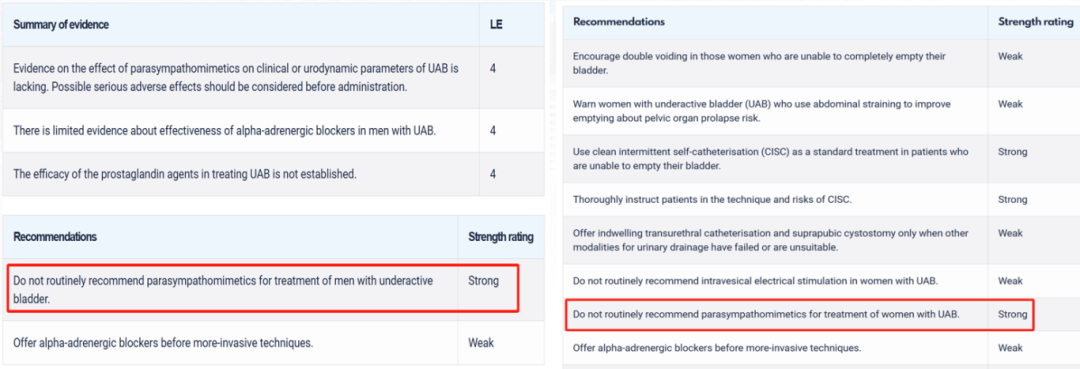
目前还没有一个药物证实是对UAB确实有效的。
增加逼尿肌的收缩力:M受体激动剂(卡巴胆碱)和乙酰胆碱酯酶抑制剂(溴吡斯斯明) 降低膀胱出口的阻力以促进尿液排出:a受体阻滞剂,尿道肉毒素注射
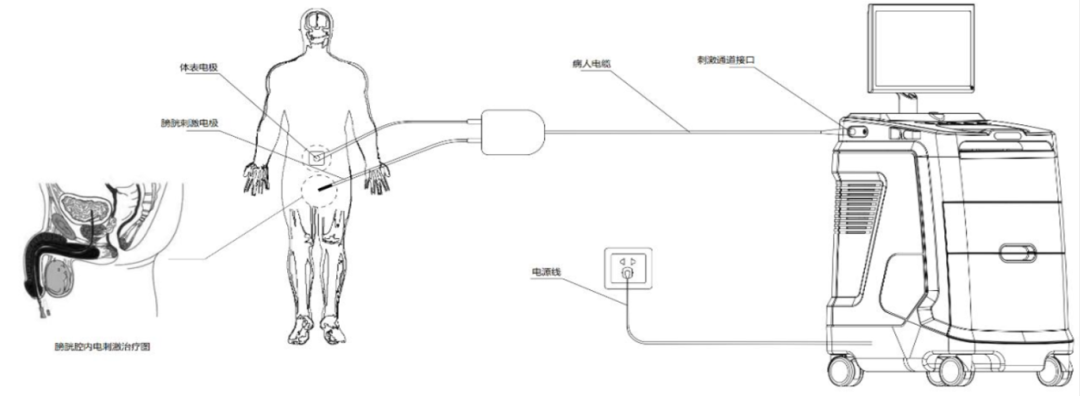
膀胱腔内电刺激(Intravesical electrical stimulation,IVES)是一种电刺激技术,可刺激A-delta机械感受器传入神经,从而增强膀胱收缩,可增加膀胱感觉,促进膀胱排空,减少残余尿。

体外冲击波疗法(Extracorporeal Shock Wave Therapy ,ESWT)可改善血管新生和组织再生,理论上可改善逼尿肌收缩性。

可能机制:激活传入感觉通路、调节-激活中枢神经系统以及抑制保护反射。
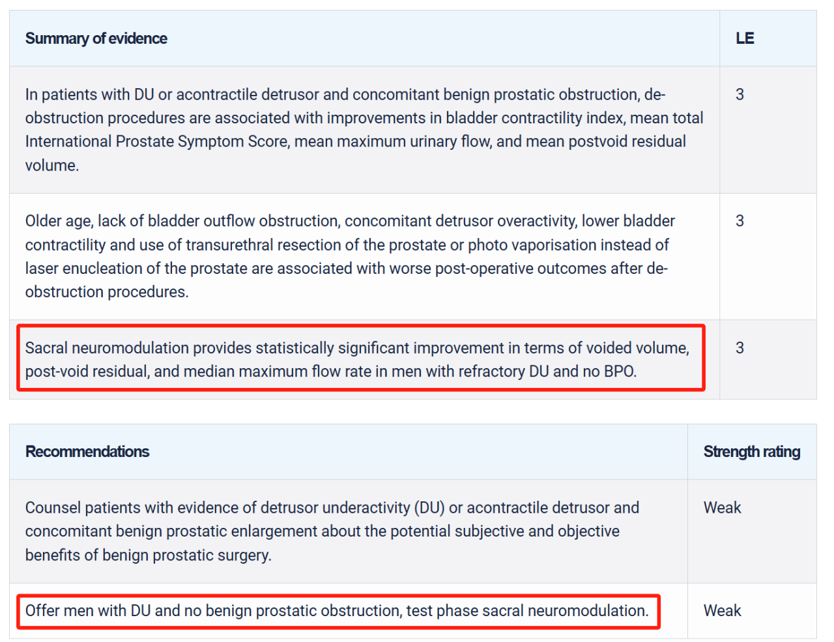
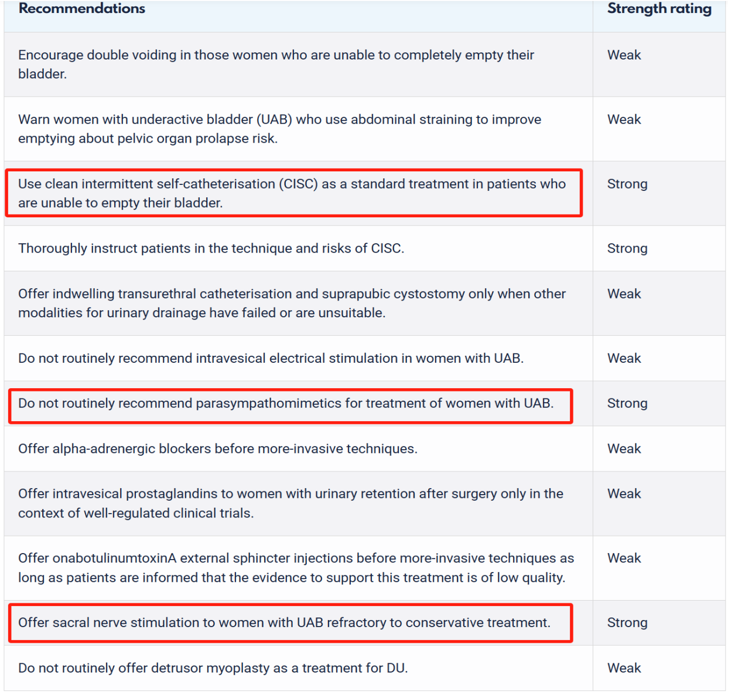

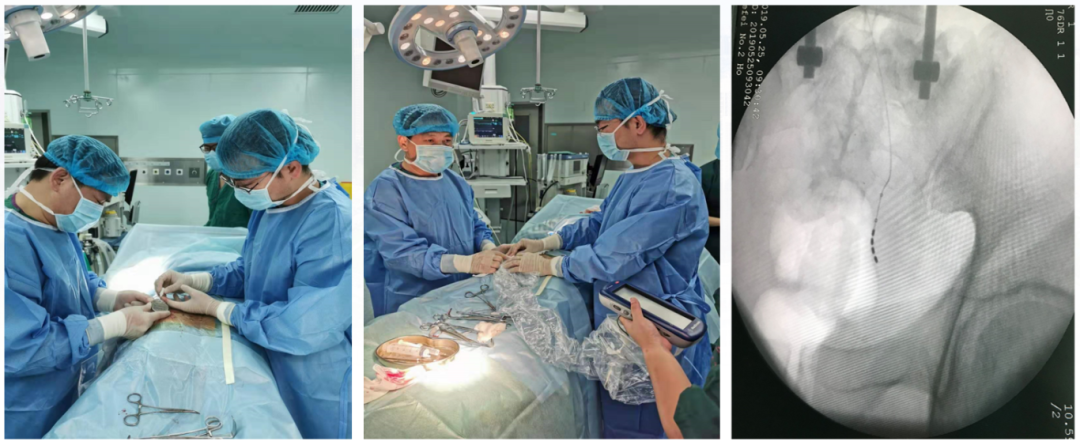
BPH行外科手术的指征是先通过尿动力学检查确定BOO存在。

UAB的治疗-IVES联合Surgery for BPO

手术治疗(LDDM)
背阔肌逼尿肌成形术(latissimus dorsi detrusor myoplasty)

手术治疗(RADM)
腹直肌逼尿肌成形术(Rectus Abdominis Detrusor Myoplasty)


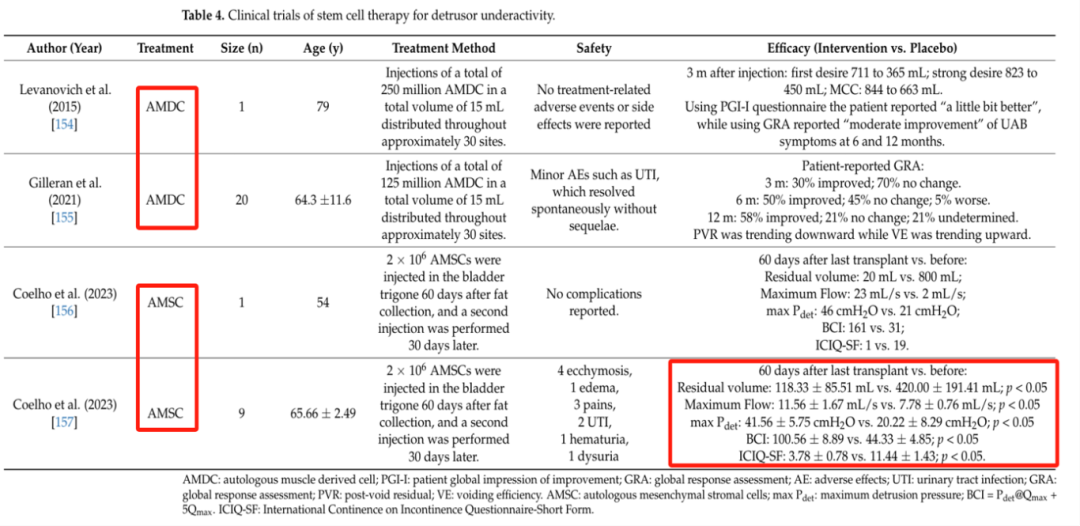
干细胞具有自我更新特性,可以在不同条件下分化成各种细胞类型。DU是由多种病因引起的逼尿肌丧失或收缩性降低引起的。因此,将干细胞注入膀胱壁治疗DU是一种有前景的治疗方法。
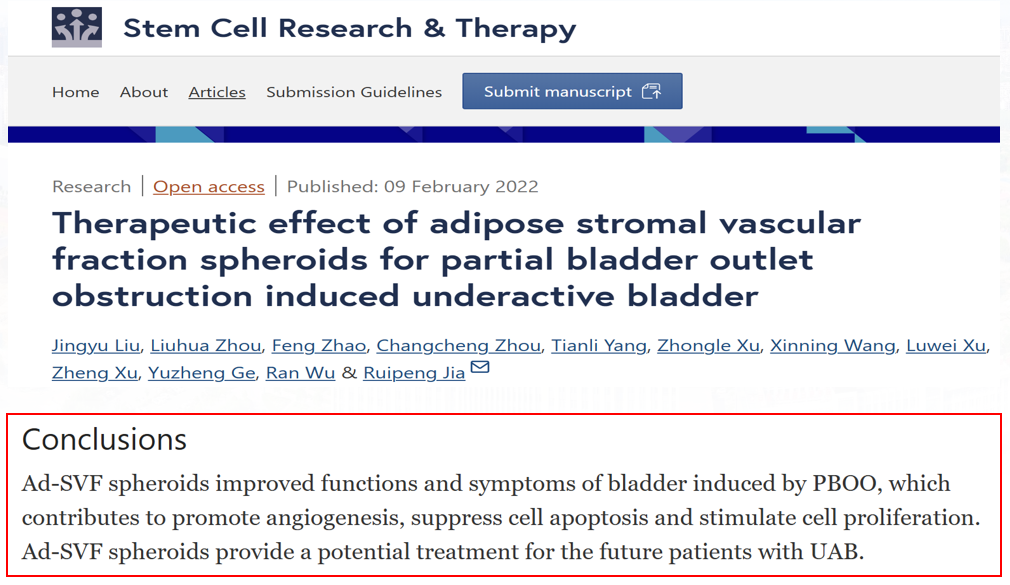
脂肪源基质血管成份( Adipose derived stromal vascular fraction , ad-SVF)为机体脂肪组织中的一组不成熟细胞群的总称,为一种新型干细胞源。
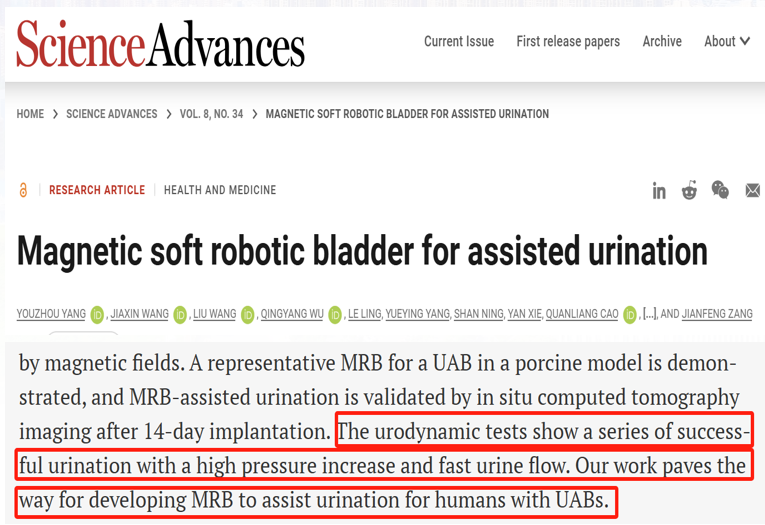
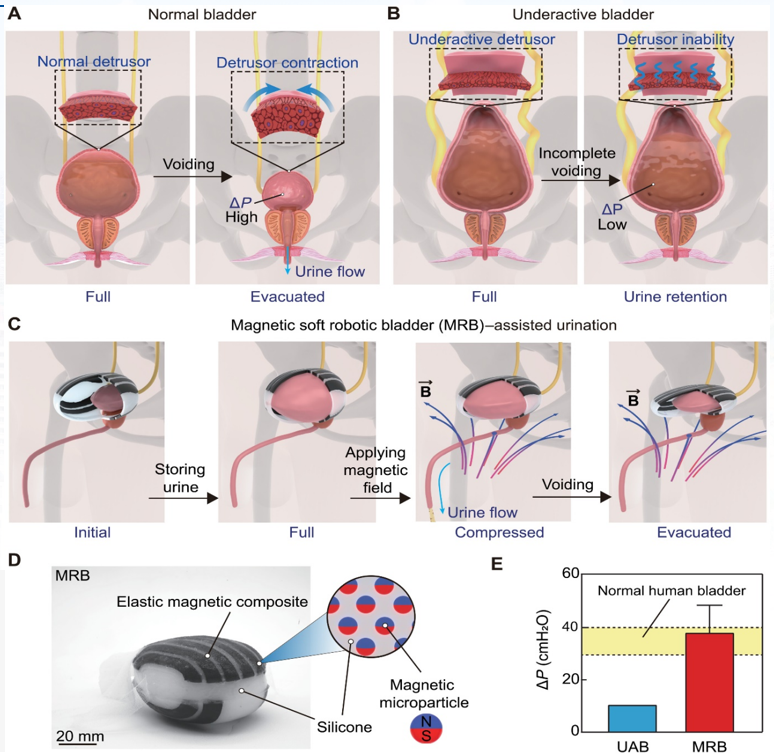
提出了一种可植入的磁性软机器膀胱(MRB),能够在UAB模型猪身上直接对膀胱施加机械压缩,从而辅助排尿过程。
描述了一种无线、完全可植入和可扩展的电子复合体,该复合体在动物模型中得到了验证,可以监测膀胱功能,并基于反馈控制系统提供电刺激以诱导排尿。


分析患者的PFS结果时不要轻易下UAB、DU及AcD的诊断
如果确实存在低压-低流、无反射等UAB的情况,必须结合直肠指检、B超、膀胱镜等综合手段判断是否存在解剖性BOO
手术指征:确诊BOO存在,同时膀胱感觉和排尿反射应该存在
手术时机:确定手术后,越早施行越好,急性尿潴留患者至少开放尿管引流2-3周
手术方式:选择解除BOO越彻底的方法
术后可以采取一些辅助措施来治疗UAB
术前应明确逼尿肌收缩力状态,以此决定术中吊带的紧张度
如果患者以OAB为主,则在治疗OAB的同时积极处理UAB,患者有可能获得自主排尿的机会
如果患者以UAB为主,则在治疗OAB之前或者同时训练患者掌握间歇导尿以排空膀胱
加强对患者的健康教育,特别是对神经系统疾病和糖尿病患者等关键人群。
应建立UAB症状与尿动力学DU之间的关系。
需要前瞻性队列研究来阐明UAB的自然史。
设计可靠的问卷,探索UAB的非侵入性诊断方法。
需要进行多中心大规模随机对照试验,以确定新药或治疗方法的安全性和有效性。
需要研究基于病理生理机制的药物靶点,包括膀胱缺血、氧化应激、炎症和纤维化。
鼓励研发膀胱置换装置。
Osman NI , Chapple CR , Abrams P ,et al. Detrusor underactivity and the underactive bladder:a new clinical entity? A review of current terminology,definitions,epidemiology,aetiology,and diagnosis[J]. Eur Urol, 2014,65:389-398.
Li X , Liao L . Updates of underactive bladder:a review of the recent literature[J]. Int Urol Nephrol, 2016,48:919-930.
Valente, S., DuBeau, C., Chancellor, D. et al. Epidemiology and demographics of the underactive bladder: a cross-sectional survey. Int Urol Nephrol 46 (Suppl 1), 7–10 (2014).
Jeong SJ, et al. Prevalence and clinical features of detrusor underactivity among elderly with lower urinary tract symptoms: a comparison between men and women[J].Korean J Urol, 2012, 53:342-34.
Smith PP . Aging and the underactive detrusor:a failure of activity or activation?[J]. Neurourol Urodyn, 2010,29:408-412.
Egilmez T , Resit Goren M . Catheterized uroflowmetry as a noninvasive test for detrusor acontractility[J]. Urol Int, 2014,92:316-322.
Li X , Liao LM , Chen GQ ,et al. Clinical and urodynamic characteristics of underactive bladder:data analysis of 1726 cases from a single center[J]. Medicine (Baltimore), 2018,97:e9610.
Osman, N.I., et al. Detrusor Underactivity and the Underactive Bladder: A Systematic Review of Preclinical and Clinical Studies. Eur Urol, 2018. 74: 633.
Liao L, Deng H, Chen G, Chen H, Huang M, Xie K, Wei X, Xu Z, Huang B, Chong T, Chen Q, Xiao H, Huang Z, Jiang H, Jing H. Randomized controlled trial of intravesical electrical stimulation for underactive bladder. BJU Int. 2023 Mar;131(3):321-329.
Shen YC, Chen CH, Chancellor MB, Chuang YC. Prospective, Randomized, Double-blind, Placebo-controlled, Pilot Study of Extracorporeal Shock Wave Therapy for Detrusor Underactivity/Underactive Bladder. Eur Urol Focus. 2023 May;9(3):524-530.
Coolen RL, Groen J, Stillebroer AB, Scheepe JR, Witte LPW, Blok BFM. Two-Staged Sacral Neuromodulation for the Treatment of Nonobstructive Urinary Retention: A Multicenter Study Assessing Predictors of Success. Neuromodulation. 2023 Dec;26(8):1823-1830.
Zhu Y, Zhao YR, Zhong P, Qiao BM, Yang ZQ, Niu YJ. Detrusor underactivity influences the efficacy of TURP in patients with BPO. Int Urol Nephrol. 2021 May;53(5):835-841.
全晶,薛文彬,黄新冕,等. 绿激光前列腺剜除术对伴有逼尿肌收缩力低下的前列腺增生患者的疗效分析. 中华泌尿外科杂志,2024,45(01):18-23.
Forte AJ. Latissimus dorsi detrusor myoplasty for bladder acontractility: a systematic review. Arch Plast Surg. 2021 Sep;48(5):528-533.
Gakis G. Functional detrusor myoplasty for bladder acontractility: long-term results. J Urol. 2011 Feb;185(2):593-9.
Agarwal P. Rectus abdominis detrusor myoplasty (RADM) for acontractile/hypocontractile bladder in spinal cord injury patients: Preliminary report. J Plast Reconstr Aesthet Surg. 2018 May;71(5):736-742.
Liu, J., Zhou, L., Zhao, F. et al. Therapeutic effect of adipose stromal vascular fraction spheroids for partial bladder outlet obstruction induced underactive bladder. Stem Cell Res Ther 13, 68 (2022).
Youzhou Yang et al.Magnetic soft robotic bladder for assisted urination.Sci. Adv.8,eabq1456(2022).
Lee JH, Hwang SW. Wireless, Fully Implantable and Expandable Electronic System for Bidirectional Electrical Neuromodulation of the Urinary Bladder. ACS Nano. 2023 May 9;17(9):8511-8520.
讲者简介 声明:本内容仅供医学药学专业人士阅读,不构成实际治疗建议。转载请后台联系授权,侵权必究! 编辑:吴梦霞 审核:黄鹏程